
Hospital at Home in Deutschland:
Chancen, Herausforderungen & Perspektiven
Hospital at Home in Germany: opportunities, challenges & prospects
Die Entlassung aus dem Krankenhaus markiert in Deutschland oft das Ende der Versorgung. Der Patient wird in ein Vakuum entlassen, das durch unklare Verantwortlichkeiten, fehlende Kontrolle und hohe Rückfallquoten gekennzeichnet ist.
Dabei gibt es längst eine bessere Lösung, medizinisch wie ökonomisch:
Telemedizinische Technologie und Hospital-at-Home-Programme füllen das Vakuum zwischen stationärer und ambulanter Versorgung – oder ersetzen den Krankenhausaufenthalt gleich ganz.

Definition: Was ist Hospital-at-Home?
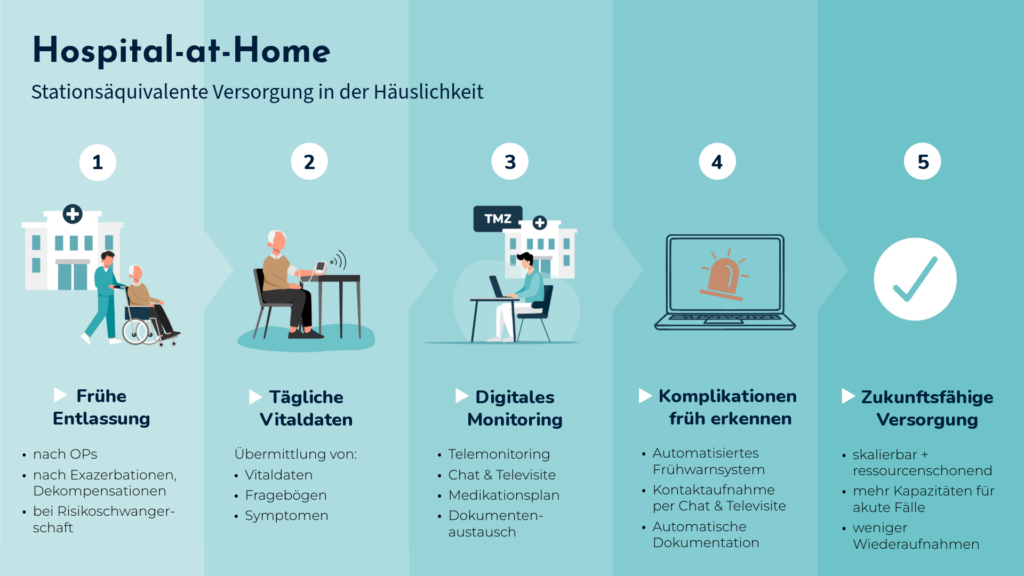
Das Hospital-at-Home ist die medizinische Versorgung von Patienten in ihrer häuslichen Umgebung auf Krankenhausniveau. Diese Versorgung zu Hause ersetzt einen stationären Aufenthalt
- ganz – durch die Vermeidung einer Aufnahme
- oder teilweise – durch eine frühere Entlassung.
1. Die Klinik bleibt medizinisch verantwortlich
Der Patient ist formal weiterhin Patient des Krankenhauses. Ein Klinikarzt entscheidet über die Aufnahme ins Programm, legt die Therapie fest und macht bei Bedarf Visiten vor Ort oder per Video. Im Notfall ist ein Bereitschaftsdienst rund um die Uhr erreichbar.
2. Der gesundheitliche Zustand des Patienten wird digital überwacht
Die Patienten messen jeden Tag selbständig Vitalparameter wie Blutdruck, Puls oder Lungenfunktion mit digitaler Sensorik und beantworten digitalisierte Fragebögen zu ihren Beschwerden per App (Telemonitoring). Diese Gesundheitsdaten werden automatisiert an die Klinik übermittelt und ausgewertet. Bei kritischen Werten kann die Klinik die Therapie frühzeitig anpassen.
3. Ambulante Dienste ergänzen die Versorgung vor Ort
Mobile Pflegedienste übernehmen bei Bedarf regelmäßige Hausbesuche, Medikamentengabe oder pflegerische Maßnahmen.
The result: Hospital-at-Home enables close-knit, intersectoral and efficient digital aftercare - without a hospital bed, but with clinical standards.
Fachbereiche: Wo Hospital-at-Home besonders gut funktioniert
1. Innere Medizin: Pneumologie & Kardiologie
Hier ist das Konzept international am weitesten verbreitet. Typische Patienten haben eine COPD-Exazerbation, eine Lungenentzündung oder eine dekompensierte Herzinsuffizienz. Ihr Zustand lässt sich gut über wenige Messwerte verfolgen: Sauerstoffsättigung, Lungenfunktion, Puls, Blutdruck und Gewicht. Verschlechtert er sich, zeigt sich das meist früh in den Daten, und die Klinik kann reagieren, bevor es zum Notfall kommt.
2. Geburtshilfe: Risikoschwangerschaften
Schwangere mit Bluthochdruck, beginnender Präeklampsie oder Schwangerschaftsdiabetes liegen oft wochenlang zur Beobachtung in der Klinik, obwohl sie kaum behandelt werden müssen. Zu Hause können sie Blutdruck, Blutzucker, Gewicht und Beschwerden selbst erfassen. Die Klinik behält die Werte im Blick, und die Frauen bleiben in ihrem Alltag und bei ihrer Familie.
3. Onkologie
Während einer Chemo- oder Immuntherapie können jederzeit Nebenwirkungen wie Fieber, Übelkeit oder Atemnot auftreten. Mit täglichen Symptomfragebögen und Vitalwerten fallen Komplikationen früher auf und lassen sich oft ambulant abfangen. Die Patienten verbringen weniger Zeit im Krankenhaus, was gerade für Krebspatienten eine große Entlastung bedeutet.
3 reasons why clinics should focus on digital care models now
The challenges in everyday hospital life are well known: rising patient numbers, a shortage of skilled staff, limited bed capacity. At the same time, hospitals need to ensure a high quality of care - not only during the inpatient stay, but also afterwards.
- The future of patient care is hybrid
Telemedical hospital-at-home programmes enable modern, patient-centred care that brings hospital standards into the living room. Those who invest today are positioning themselves as pioneers in a healthcare system that is increasingly focussing on outpatient, digital and flexible care models.
- Resource bottlenecks in clinics require new care pathways
In the face of cost pressure, a shortage of specialist staff and overcrowded hospitals, telemonitoring programmes offer an effective way of conserving inpatient capacity without compromising on quality. Telemonitoring ensures safety and control - even outside the hospital walls.
- Sector boundaries can be overcome digitally
Digital care models such as hospital-at-home promote close collaboration between hospitals, GP practices and outpatient services. Structured task planning and the digital exchange of relevant health data create a seamless flow of information - for more efficient care without frictional losses at the interfaces.
Telemedicine in hospitals: 2 examples from Germany
Example 1:
The Telemedicine centre of the Robert Bosch Hospital cares for patients with chronic heart failure and COPD. The combination of vital data monitoring and personal telephone support enables close follow-up care - with positive effects on quality of life and security of care.
Example 2:
The Institute for Applied Telemedicine (IFAT) of the Heart and Diabetes Centre NRW (University Hospital of the Ruhr University Bochum) cares for around 11,000 patients with telemedical services.
With a newly installed telemedical programme for the care of heart patients the Institute is setting new standards in telemonitoring for heart failure.
3 ways to finance hospital-at-home in Germany
The implementation of telemedicine hospital-at-home programmes can be realised in Germany via various funding channels - depending on the strategic focus and healthcare context:
Regular outpatient HI care via an MVZ
In Germany, telemedical care has so far become part of standard outpatient care for one group of patients: the Telemonitoring for chronic heart failure. This approach is ideal for clinics that work closely with an MVZ and want to transfer inpatients to long-term outpatient care via telemonitoring after discharge.
Selective contracts with health insurance companies
Clinics and health insurance companies can agree customised care models via individual selective contracts. These contracts offer flexibility in the design of services, remuneration and quality criteria - ideal for innovative hospital-at-home programmes that go beyond standard care. They also enable close cooperation between service providers and payers.
Funding via the KHTF (cross-indication)
The Hospital Transformation Fund (KHTF) offers a strategically particularly relevant funding opportunity for the structured development of telemedical networks. The central element here is the subsidisation criteria in accordance with Section 3 (3) KHTFV for the establishment of telemedical network structures.
This subsidy provides targeted support:
- The creation of cross-sector telemedical infrastructures
- The establishment of digital supply chains between hospitals, community-based doctors and outpatient services
- Investments in interoperable telemonitoring systems and digital communication platforms
The decisive advantage: The funding is designed to be cross-indication - hospital-at-home structures can therefore be created in various specialist areas of clinical aftercare. This creates sustainable, future-proof care structures that go beyond individual clinical pictures.
Hospitals that take a strategic approach to setting up telemedicine networks now will not only secure funding, but also position themselves as key players in networked, digital healthcare.
Source:
1 Federal Ministry of Health: Hospital Care Improvement Act (KHVVG)
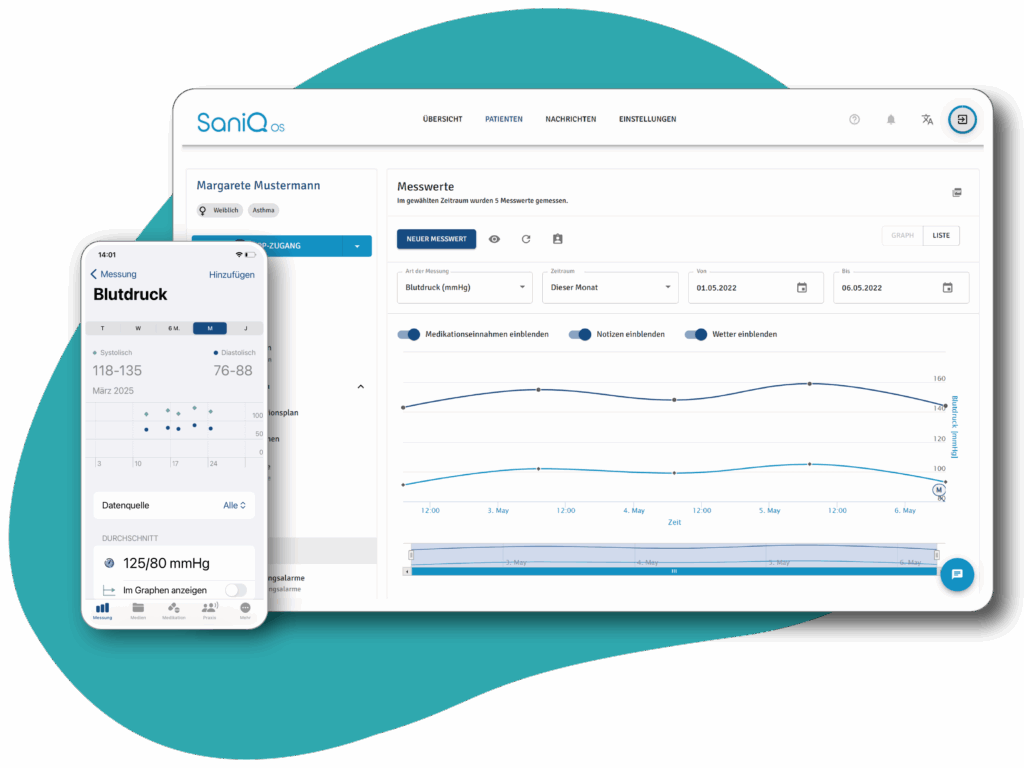
Das Hospital-at-Home auf einer Plattform
Erweitern Sie Ihre Station um virtuelle Betten und schaffen Sie Kapazitäten für beue, akute Fälle.
These articles might be of interest to you:

Future check: Telemonitoring in Germany
As a key digital medical technology, telemonitoring is central to overcoming urgent challenges in the German healthcare system. So where does Germany stand when it comes to integrating this pioneering technology into healthcare?

How digital medicine is closing the care gap for rare diseases
Innovative telemedicine applications can significantly improve the care of people with rare diseases. A team of doctors at Berlin's Charité hospital is breaking new ground to provide much-needed support to those affected by a neurological disease.
 Deutsch
 English
 English (UK)
 Français
 Italiano
 Español
 简体中文
 Nederlands
 Nederlands (België)
 Français de Belgique
 Polski
 Türkçe
 Українська